
PART 1 — THE PHARMACY BAG
My name is Robert Hale, I’m seventy-four, and the moment Dr. Elaine Porter grabbed my wrist, I knew something was terribly wrong.
My wife, Margaret, had been living with severe memory problems for seven years. After I injured my back, our grandson, Ethan, moved in to help with groceries, appointments, and her medications. I was grateful. Maybe too grateful.
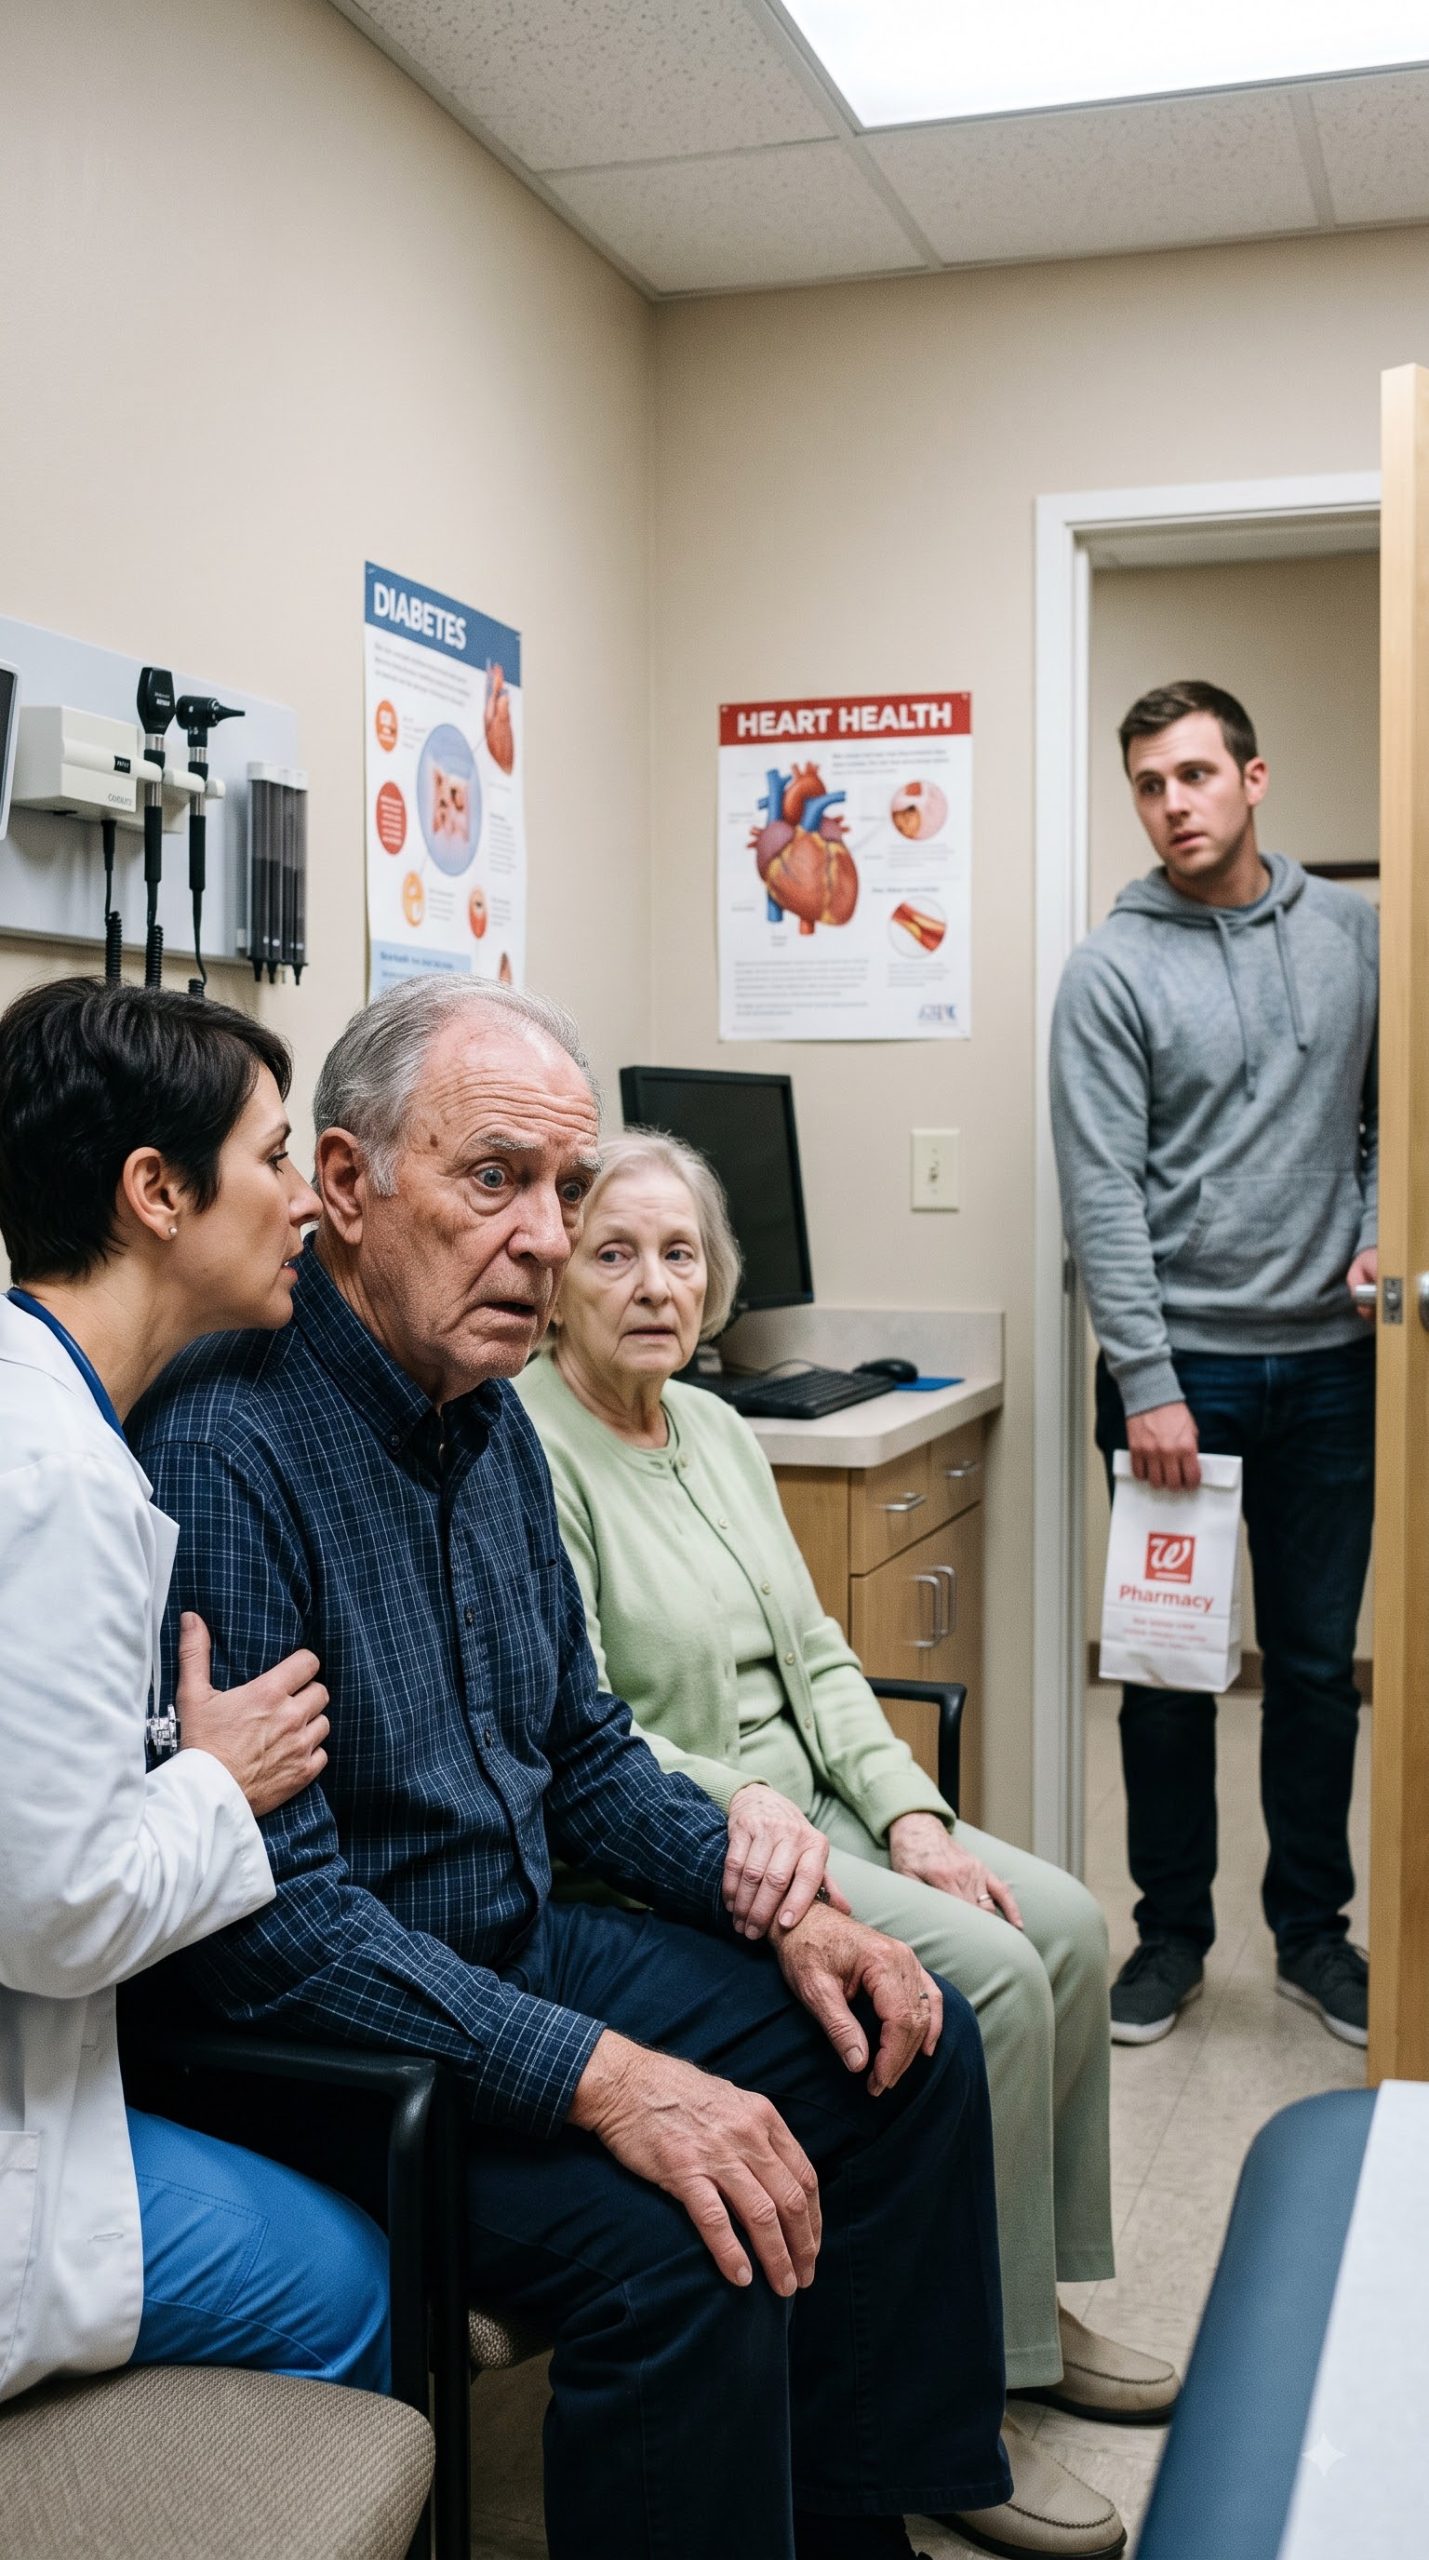
That Tuesday, I took Margaret to a new geriatric specialist because she had become unusually sleepy, confused, and unsteady. Ethan came with us and answered almost every question before Margaret could.
“She’s just getting worse,” he kept saying.
Dr. Porter watched him carefully.
Then Ethan’s phone rang.
“I need to take this,” he said, stepping into the hallway.
The door had barely closed when Dr. Porter leaned toward me.
“Mr. Hale, who gives your wife her medications?”
“Ethan organizes them.”
She turned her monitor toward me.
Margaret’s medication list showed several sedating prescriptions from different clinics, including two drugs that should never have been added without careful review.
“Were you aware of these?”
I shook my head.
Dr. Porter lowered her voice.
“I’m not saying what happened yet. But her current symptoms may be medication-related, and I need you to keep her away from anyone giving her pills until we sort this out.”
Then she gripped my wrist.
“Get her out tonight.”
Before I could ask another question, the door opened.
Ethan walked back in holding a white pharmacy bag.
“Picked up Grandma’s refill,” he said casually.
Dr. Porter’s face went pale.
“What refill?”
Ethan pulled out a bottle.
She took one look at the label.
“That medication isn’t on the plan I approved.”
Ethan’s expression changed.
“It’s from another doctor.”
“Which doctor?”
He hesitated.
Margaret looked at me, confused.
Then Dr. Porter reached for the phone.
“Mr. Hale, I want your wife evaluated at the hospital today. Bring every medication in the house.”
Ethan stepped forward.
“That’s unnecessary.”
Dr. Porter looked directly at him.
“No. What’s unnecessary is anyone giving her another pill before we know exactly what she’s been taking.”
And for the first time, I realized my grandson wasn’t frightened for Margaret.
He was frightened of what we might find.
PART 2 — WHAT WAS IN THE PILL BOX
At the hospital, a pharmacist and physician reviewed every bottle I brought from home.
There were duplicates.
There were medications prescribed months apart by different providers who apparently did not know what the others had ordered. Some had been discontinued in earlier records but were still being given.
No one said Ethan had deliberately poisoned Margaret.
But they did say the combination could contribute to extreme drowsiness, falls, confusion, and worsening cognition in older adults.
For years, I had accepted every decline as part of her condition.
Maybe some of it was.
Maybe some of it wasn’t.
A hospital social worker named Denise asked to speak with me privately.
“Who controls the pharmacy account?”
“Ethan.”
“Who picks up the prescriptions?”
“Usually Ethan.”
“Who manages your wife’s money?”
I hesitated.
“He helps us.”
That answer sounded different now.
Denise asked whether Ethan had access to our bank accounts.
I told her he had online access because he paid household bills when my back was bad.
She suggested I review recent transactions.
I opened my banking app.
There were transfers I didn’t recognize.
Small ones at first.
Then larger withdrawals.
$1,500.
$2,200.
$4,000.
All sent to an account with Ethan’s name on it.
My hands started shaking.
I called him.
He answered on the second ring.
“Grandpa, where are you?”
“At the hospital.”
A pause.
“I told you that was unnecessary.”
“What are these transfers?”
Silence.
Then he said, “You told me I could reimburse myself.”
“For groceries. Not thousands of dollars.”
He became defensive.
“I’ve given up my life to take care of you two.”
“That doesn’t answer my question.”
He hung up.
Denise helped me contact the bank’s fraud department and Adult Protective Services. I also called my attorney, Frank Mercer, and revoked Ethan’s financial access that afternoon.
Margaret stayed overnight for observation while the doctors simplified her medication plan.
The next morning, she was still confused, but noticeably more alert.
She looked at me and said, “Robert, where’s my blue sweater?”
It was a simple sentence.
But she had not asked me for anything that clearly in months.
I nearly cried.
Then my phone buzzed.
It was a security notification from our home camera.
Ethan was inside the house.
He was carrying two suitcases.
And he was opening the locked file cabinet where we kept our wills, property documents, and account records.
I showed the video to Denise.
She immediately called hospital security and told me not to go home alone.
Then Ethan sent me a message:
“Grandpa, we need to fix this before you make a mistake you can’t undo.”
PART 3 — WHAT WE FINALLY SAW
The police met me at the house.
Ethan was still there.
He insisted he was packing his own things and trying to collect documents that “proved” he had permission to manage our finances.
The problem was that the documents said nothing of the sort.
He had limited authorization to pay bills and pick up prescriptions. He did not have permission to transfer money to himself, and he certainly did not have authority to change Margaret’s medical care without telling me.
Some of the money had been used for legitimate household expenses. Some had not. Ethan eventually admitted he had used part of it to cover personal debts and told himself he deserved repayment for being our caregiver.
As for the medications, investigators never proved he intended to harm Margaret. What they established was negligence: he had continued giving old prescriptions, accepted refills from multiple providers, and never told each doctor about the full list.
That distinction mattered.
I did not want a story more dramatic than the truth.
The truth was already painful enough.
Margaret’s memory did not suddenly return. She still had a progressive cognitive illness. But once her medications were reviewed and simplified, she became more awake, steadier on her feet, and more present in conversations.
I hired a professional caregiver three mornings a week and moved all bill payments to an accountant supervised by my attorney. The bank restored what it could, and Ethan signed a repayment agreement as part of resolving the financial dispute.
For nearly a year, I didn’t speak to him.
Then one afternoon, he wrote me a letter.
“I started helping because I loved you,” he wrote. “Then I got angry that my life had become your life. I started taking money and telling myself it was fair. I was wrong.”
I believed the apology.
I did not restore his access.
Forgiveness and access are not the same thing.
Six months later, he visited Margaret with me present. She didn’t fully remember what had happened, but she smiled when she saw him.
“Have you been behaving?” she asked.
Ethan laughed once, then started crying.
“I’m trying, Grandma.”
So are we.
What happened taught me something I wish I had understood sooner: when an older person depends on family, love needs oversight too. Trust is important, but clear records, shared information, and boundaries protect everyone.
If someone you loved was caring for an aging parent but started controlling the medications and money, would you confront them privately first—or bring in doctors, lawyers, and authorities immediately?
Tell me what you would do. I think American families would have very different answers.


